This guide explains Mulhenua as a concept tied to dental implant planning and decision-making, then walks readers through how people commonly reduce implant costs in English-, Spanish-, and Portuguese-speaking countries. It compares reputable information sources, outlines a step-by-step process, and provides reference price ranges by country and currency—while emphasizing clinical fit, safety, and provider verification.
Mulhenua is best understood here as a shorthand for a patient-centered approach to dental implant planning: evaluate fit, transparency, and long-term outcomes rather than focusing only on the initial invoice. In practical terms, Mulhenua encourages readers to compare treatment pathways (single-tooth implants, multi-unit restorations, and full-arch options), confirm clinical indications, and verify whether “low-cost” offerings still maintain essential standards such as appropriate diagnostics, sterilization protocols, and restorative planning.
For patients searching for low-cost dental implants, the challenge is consistent across regions: the cheapest option is not always the most economical over time. The goal of this guide is therefore objective—help you understand where cost differences arise, how to approach pricing responsibly, and which reputable online resources can support comparisons in English-, Spanish-, and Portuguese-speaking markets.
Mulhenua-style planning also acknowledges that “implant care” is not a single event; it is a structured sequence involving diagnosis, surgical execution, healing supervision, and prosthetic design. If one link in the chain is unclear—such as what imaging is used, which implant system is offered, or whether follow-up is included—then the true cost may not be visible until complications or adjustments arise later. That is why Mulhenua elevates transparency and documentation as much as affordability.
Throughout this guide, you’ll see how to ask better questions, interpret what you’re being quoted, and compare options across different clinical realities. Whether you are paying locally or considering cross-border treatment, the “Mulhenua lens” remains the same: insist on a match between your anatomy and the proposed plan, insist that the plan is clearly documented, and insist that the promised outcome is supported by responsible follow-up and maintenance.
Dental implants are not a single product; they are a multi-stage clinical pathway. Costs differ due to a combination of factors that can include:
From an industry perspective, a “low-cost” claim is most meaningful when it clarifies what is included (consultation, imaging, surgery, prosthetic components, and follow-up) and what is not. A transparent package structure often reduces the likelihood of unexpected add-ons after the procedure begins.
It also helps to understand what patients often underestimate. For example, a lower headline price for a “standard implant” may not include preparatory procedures such as periodontal maintenance, infection management, or bone grafting. Conversely, a higher quote might include grafting contingency, provisional teeth, and more detailed planning. Over time, those inclusions can materially affect your total spending and the predictability of outcomes.
Another common reason costs diverge is the restorative philosophy. Two clinics may place the same number of implants, but one may design the prosthesis to protect the implant-bone interface through better load distribution and occlusal planning, while another may treat the restoration as an afterthought. Even if the immediate price difference seems small, the downstream cost of remakes, repeated adjustments, or additional repairs can shift the economics dramatically.
Finally, surgical approach can change costs. For instance, clinicians may use guided surgery (template planning based on imaging) that can increase planning time but potentially improve placement accuracy in complex cases. Whether that approach is necessary depends on your anatomy and the implant plan. A low-cost provider might not use guided surgery in routine cases, which could lower upfront fees—yet it may still be appropriate for some patients. Mulhenua therefore encourages evaluating appropriateness and documentation rather than assuming that “more technology” automatically means “better care.”
People commonly reduce out-of-pocket dental implant costs through one (or a combination) of the following routes:
In the sections below, you’ll find a structured comparison of online resources and how they position cost and implant decision support. The intent is to help you compare like-for-like information—an essential part of Mulhenua-style planning.
To apply Mulhenua effectively, it’s useful to distinguish between “information that helps you decide” and “marketing that pushes a decision.” Some websites focus on describing treatment steps clearly, offering checklists, and explaining what is included in pricing packages. Others are more promotional, emphasizing price reductions without sufficiently clarifying diagnostic standards, component transparency, or follow-up commitments. A Mulhenua-aligned reader uses the former as a tool for questioning and comparison, while remaining cautious with the latter.
Insurance strategies also require careful interpretation. Even when implants are not fully covered, insurers may cover diagnostic imaging, cleanings, periodontal therapy, or certain preparatory steps. If you plan around what your policy covers, your out-of-pocket total may decrease without compromising implant care. However, some patients lose money when they proceed with a plan that later turns out to be non-eligible for reimbursements due to missing documentation or timing requirements.
Similarly, dental tourism can be cost-effective, but only when records and follow-up are handled deliberately. If your travel provider does not plan for continuity—such as how you will receive management for complications after you return home—then the apparent savings can disappear. Mulhenua therefore stresses continuity planning: the provider should be willing to share records, explain postoperative protocols clearly, and discuss contingency plans.
Below is a compact comparison of several websites that provide information relevant to low-cost dental implants. This table focuses on the type of information each site tends to provide (not on replacing clinician judgment).
| Website | Typical Focus for Cost-Related Information |
|---|---|
| dentalviews.com | Low-cost implant education, treatment pathways, and cost considerations |
| atlanticdentalgrp.com | Clinic service overview including implants, scheduling, and broader care options |
| dentavacation.com | Dental tourism framing: cross-border procedure planning and cost comparison |
| rockvilledentalarts.com/es | Insurance-oriented guidance and consumer explanation of implant-related coverage concepts |
source: www.dentalviews.com
source: www.atlanticdentalgrp.com
source: www.dentavacation.com
source: www.rockvilledentalarts.com/es
To go one step further than the table, Mulhenua suggests using these sites as starting points to draft the questions you will bring to a clinic. For instance, if a low-cost implant article describes that imaging is sometimes included and sometimes not, you can use that detail to ask your provider: “Which imaging is included, and what happens if additional imaging is necessary?” If a tourism platform explains that treatment timelines may vary by clinic capacity, you can ask: “What is the exact sequence of visits, and how do you manage potential delays?”
The key is not to accept a website’s pricing statements as final. Instead, treat them as hypotheses to test with written scopes of treatment and clinical documentation. Mulhenua is essentially “evidence-driven consumerism”: you verify what you can, document what you receive, and avoid relying on vague promises.
Implant planning requires accurate communication—about symptoms, medical history, imaging findings, and follow-up expectations. For Mulhenua-aligned decision-making, using language-appropriate resources can improve comprehension and reduce misunderstandings when discussing treatment steps, consent forms, and aftercare routines.
In Spanish-speaking settings, for example, patient-facing explanations may highlight implant options alongside commonly requested services such as whitening, cleaning, orthodontics, and emergency care. In Portuguese-speaking markets, clinics and plan providers often emphasize a broader network model or clinic specialization depending on location and patient needs.
Language also matters for consent quality. Many complications—such as delayed healing, infection, or the need for additional procedures—require careful explanation. If a patient does not fully understand the postoperative restrictions (diet, hygiene, smoking considerations, medication schedules, or activity limitations), the risk of avoidable problems increases. That is why localized resources can indirectly affect outcomes even before you choose a clinic.
Mulhenua therefore encourages readers to ask for written documentation in their preferred language whenever possible. If your clinic provides documents only in the local language, request a translated summary of the key points: implant type, expected timeline, immediate postoperative care, warning signs that require urgent contact, and the maintenance schedule. This is not merely convenience; it is risk management.
English-speaking countries often rely on educational implant pages, clinic service listings, and dental tourism comparison frameworks. For readers in these regions, information sources may differ in style but generally aim to reduce uncertainty about implant steps, inclusion/exclusion of fees, and basic eligibility considerations.
Spanish-speaking countries frequently benefit from Spanish-language clinic or insurance explanations. Language-localized content can be especially important when discussing implant concepts such as osseointegration, prosthetic timelines, and post-operative restrictions.
Portuguese-speaking countries commonly encounter a mix of clinic-based services and plan-based offerings. Some providers emphasize multiple specialties (orthodontics, esthetics, implants), while others focus on plan networks and emergency coverage continuity.
Despite differences in marketing style, the decision criteria for Mulhenua remain consistent. The best “low-cost” pathway is the one that aligns with your anatomy and health while offering transparency about included diagnostics, components, follow-up, and maintenance. Any region can produce either excellent value or misleading pricing; the difference is not location, but documentation and clinical responsibility.
Note: Because the placeholder {lang} was not explicitly provided, the steps below are written in a way that applies across English-, Spanish-, and Portuguese-speaking countries—where the practical process is broadly similar. If you tell me your target language/country set, I can tailor the guidance to match local terminology and typical clinic workflows.
Ask for a diagnostic plan that clarifies whether you need a standard implant, grafting, or alternative treatment. Low cost is only meaningful if the implant is biologically appropriate for your bone volume and health profile.
Mulhenua rationale: an ineligible implant plan can look inexpensive initially but become expensive due to revision surgery, prolonged healing, or alternative treatments later.
Before comparing quotes, insist on a breakdown: imaging, surgical procedure details, implant components included, prosthetic type (crown/bridge/implant-supported denture), and follow-up appointments.
What to look for in the document: explicit visit counts and stages. For example, “surgery day,” “suture removal,” “healing check,” “prosthesis delivery,” and “adjustment visits.” Vague “as needed” language can be appropriate clinically, but it should still be paired with an estimate or an agreed approach.
In many best-practice settings, CBCT or equivalent imaging is used to plan implant placement and reduce avoidable complications. Confirm what imaging is included in the package.
Additional Mulhenua tip: ask whether imaging is used for both surgical planning and prosthetic planning. If a clinic provides imaging but does not use it for prosthetics (for example, neglecting the planned emergence profile), restorative problems can increase.
Two quotes can list the same number of implants while differing in abutments, crown materials, and lab design—affecting longevity and cost over time.
Common cost-related differences include zirconia vs other materials, monolithic designs vs layered designs, and whether the lab includes a full digital workflow. These choices can change both strength and aesthetics, which influences long-term maintenance.
In some markets, dental insurance may cover exams, cleanings, x-rays, or certain preparatory treatments. Even when implant coverage is limited, planning around covered services can reduce overall out-of-pocket expenses.
Mulhenua suggestion: request pre-treatment documentation when possible. If the insurer requires authorization, do not proceed on the assumption that “they’ll approve later.”
If you consider travel, prioritize a provider that offers documented treatment plans, clear aftercare instructions, and a realistic follow-up schedule (including how complications are handled).
Practical continuity questions: Will they provide copies of CBCT or imaging reports? Will they name the implant system and lot numbers? Will they share prosthetic specifications for a local dentist to reference during follow-up?
Clarify who performs surgery, who manages healing follow-up, and who constructs the prosthesis. Consistent clinical responsibility reduces risk and communication gaps.
Mulhenua framing: confirm the “chain of custody” for your care. You should know which clinician is responsible for which stage and who to contact if something changes.
Low cost should not remove essential maintenance planning. Ask whether there is a prosthetic adjustment process if the bite needs tuning during healing.
In addition to warranties, ask about maintenance schedule expectations. Implants require professional checkups and hygiene. Some clinics include a defined follow-up interval; others expect you to return to your own dentist or pay separately.
Keep copies of imaging reports, implant component details, prosthetic specifications, and any insurance documents. This helps continuity if you move or change providers.
Mulhenua reminder: your documentation becomes part of your future decision-making. It makes second opinions easier and helps you maintain continuity if you return for additional restorative work.
The table below provides reference price ranges for individual dental implants only. Actual quotes vary based on clinical complexity, prosthetic requirements, and what is included in the package.
| Country | Currency | Price Range (Single Implant) |
|---|---|---|
| United States | USD | $3,000 - $6,000 |
| United Kingdom | GBP | £2,000 - £2,500 |
| Australia | AUD | AU$3,500 - AU$6,500 |
| Canada | CAD | CA$3,000 - CA$5,500 |
| Spain | EUR | €1,500 - €2,500 |
| Chile | CLP | CLP$800,000 - CLP$1,500,000 |
| Mexico | MXN | $15,000 - $25,000 |
| Colombia | COP | $2,000,000 - $4,000,000 |
| Peru | PEN | S/ 3,000 - S/ 6,000 |
| Argentina | ARS | $80,000 - $150,000 |
| Brazil | BRL | R$3,000 - R$8,000 |
| Portugal | EUR | €1,000 - €2,000 |
Mulhenua interpretation: treat these as orientation points, not guarantees. A “low-cost” provider offering a price far below the reference range may be using a different scope (for example, not including imaging, not including a permanent crown, or not including follow-up). Conversely, a quote above the range could include more diagnostics, better restorative materials, or additional preparatory treatments. The question is always: what is included, and is it appropriate for your clinical situation?
If you are comparing providers within a single country, it can also be useful to ask whether a quote includes:
Industry experience shows that “cheap” can mean different things: a lower surgical fee, a different prosthetic design, or a streamlined pathway. Mulhenua-style comparison therefore emphasizes what is included and who provides each service. When reviewing a clinic or plan, consider the following checklist.
Additional Mulhenua detail: ask if the clinic discusses risk factors. For example, if you have a history of periodontitis, smoking, diabetes, uncontrolled gum inflammation, or inadequate oral hygiene access, your care plan should reflect those realities. A low-cost offer that ignores risk factors can be low-cost for a reason.
Coordination matters because implants fail less from the act of placement alone and more from a mismatch between healing and restorative loading, or from inadequate infection control during and after surgery. Even if the surgical technique is sound, follow-up quality affects outcomes. A quote that seems inexpensive but does not include healing monitoring may raise the risk of missed early warning signs.
In Mulhenua terms, transparency is a form of risk reduction. When a clinic provides detailed component information, it becomes easier for another clinician to support you later if needed. When a clinic is vague—offering an “implant included” price but without naming the implant system—continuity becomes harder and repair costs can increase.
A Mulhenua-aligned provider explains not only what they will do, but what they will do if things do not go as planned. Responsible consent includes a realistic acknowledgment of variability in healing and the possibility of adjustments. A clinic that avoids discussing complications may be less prepared to manage them later.
Different regions develop different market patterns for pricing and service delivery. For example:
However, pricing differences should not be interpreted as differences in clinical quality. A responsible comparison evaluates documented clinical protocols, the clinician’s experience, and how the plan manages follow-up and complications.
To avoid overpromising, it can help to adopt a neutral evaluation approach. Mulhenua encourages you to treat each quote as a “proposal that must be verified.” For example:
A: In many cases it refers to a packaged fee structure that may include consult, imaging, surgery, and a prosthetic component. The key is to request a written breakdown. “Low cost” can change based on whether bone grafting, temporary crowns, additional visits, or certain materials are included.
A: Not directly. Even when reference price ranges exist, total cost depends on clinical complexity, restorative materials, and whether preparatory treatments are needed. Comparing itemized quotes is more reliable than comparing headline numbers.
A: Sometimes. Many plans cover exams, x-rays, cleanings, and preventive services, and may partially cover specific treatments. Coverage for implants varies widely by policy and clinical indication, so consumers should verify benefits and request written confirmation.
A: It can be reasonable for some patients if the provider offers transparent documentation, clear treatment timelines, and robust follow-up planning. Safety depends on continuity of records, aftercare instructions, and how complications are managed if they occur after travel.
A: Mini implant systems exist and may be suitable for select cases, often where the clinical situation matches the design indications. Suitability depends on bone conditions, load distribution needs, and restorative planning—so eligibility must be evaluated by a clinician.
A: Implant longevity depends on surgical success, restorative design, oral hygiene, and maintenance. Clinically sound follow-up and patient adherence to hygiene and checkups are strongly associated with outcomes, but exact duration varies by case.
A: Ask for (1) a written treatment plan, (2) what is included in the quoted price, (3) imaging type used, (4) who will perform each stage, (5) timeline for healing and restoration, (6) risks and contingency plans, and (7) follow-up and warranty/maintenance terms for the prosthesis.
A: Not necessarily. A well-run clinic may lower prices through efficient workflows, transparent packages, and economies of scale. The safer approach is to evaluate protocols and documentation rather than price alone.
Low-cost strategies often come with practical constraints. To protect your investment—financially and clinically—expect that providers may require:
These requirements can be frustrating for patients who want a quick fix. However, they are often the reason low-cost programs can still be safe. For example, screening may limit low-cost offerings to patients whose anatomy supports a predictable surgical approach. When you understand that screening exists for quality reasons, you can align your expectations and reduce the chance of “scope drift” later.
Mulhenua also suggests that patients think about opportunity cost: if a low-cost provider requires more visits not included in the package, it can add labor and time costs that are not reflected in the invoice. Your decision should consider not only money, but also time, travel, and the impact on your daily schedule.
To turn pricing comparisons into a real decision, use this shortlist:
Mulhenua can be even more effective if you convert the checklist into a standardized request message. For example, you can ask clinics to respond in the same order: imaging included, implant system/parts included, surgery visits included, prosthesis material/specification included, warranty terms, and follow-up appointment schedule. This “structured comparison” approach reduces the chance that two clinics are accidentally comparing different scopes of care.
Another practical approach is to request a “package boundary statement.” Ask: “If my case changes (for example, additional grafting becomes necessary), what additional costs apply and how will that be approved?” Responsible clinics should be able to explain these boundaries clearly, even if final costs cannot be known before surgery. The goal is to prevent surprise expenses and to protect your ability to plan financially.
Mulhenua’s central claim is not “avoid low-cost care.” It is “avoid unclear care.” Many patients instinctively assume that a lower price indicates lower quality. In reality, value can exist at many price points. The challenge is that risk is often hidden in what is omitted or what is left undefined.
Below are concrete ways to identify whether a “low-cost” implant offer is delivering true value or simply transferring uncertainty onto you.
Patients are not expected to understand every clinical nuance. However, they are expected—under Mulhenua principles—to demand clarity about the boundaries of their care. If a clinic provides clarity, it becomes easier to trust that low cost comes from operational efficiency and transparent planning rather than from missing essential steps.
Mulhenua encourages comparing pathways, not just comparing numbers. This matters because implant economics differ by scenario.
Single-tooth implants typically involve one implant site and a crown. If the patient has adequate bone and there is no major aesthetic challenge, costs may be lower. However, low-cost packages may exclude provisional coverage, exclude certain aesthetic materials, or assume you do not need grafting.
Multi-unit restorations involve multiple implants and a bridge or other framework. The restorative plan becomes more complex because alignment, load distribution, and the design of the framework influence the stability and comfort of the prosthesis.
Full-arch options (often involving multiple implants supporting a full-arch prosthesis) introduce additional variables: the need for stable prosthetic design over a large span, occlusal planning, and frequently more structured follow-up. Full-arch pricing can appear “low” when a package includes a particular prosthetic design and uses standardized workflows. In contrast, “custom” plans may include more bespoke planning and may carry higher costs but sometimes can reduce future adjustments.
This is why Mulhenua demands that the quote specify not only implant count but also the restoration type and materials. A single-tooth and full-arch case should not be compared using the same mental model, even if both are described as “implants.”
Some patients avoid asking questions because they fear “not knowing the right terminology.” Mulhenua reframes this: you do not need clinical expertise; you need clarity. Below are question templates that work across language contexts.
Notice that none of these require you to understand implant science. They focus on deliverables, responsibility, and documentation—core Mulhenua principles.
Dental tourism can be a practical solution when local costs are prohibitive or when specialized implant programs exist abroad. Mulhenua does not automatically reject travel; it insists on continuity.
To evaluate a dental tourism package, you need answers to questions that local care sometimes handles automatically because you can simply return. When you are far away, you must create a plan for how care continues after you travel.
A low-cost tourism package can be value-positive when records transfer is smooth and follow-up is planned. It becomes value-negative when continuity is weak and the patient is left to find a provider mid-complication without documentation.
Insurance varies widely across countries and plans, but Mulhenua teaches a consistent strategy: use insurance to cover what it covers, and use your clinician to document what is needed for eligibility.
Patients often discover too late that pre-treatment approvals were required or that certain services weren’t included in the claim package. Mulhenua therefore encourages administrative clarity. Even when insurance does not cover implants fully, it may cover exams, diagnostics, and supportive dental care that improves implant success.
Practical steps include:
Then, connect that to your implant plan. If a low-cost implant offer excludes diagnostic imaging, and your insurance could cover imaging, it may still make sense overall—even if the implant package looks expensive. Mulhenua’s goal is not to maximize the clinic’s discount; it is to minimize total cost while preserving quality.
Mini implants can sometimes reduce cost or complexity in selected cases. However, suitability is highly case-dependent. Mulhenua encourages readers to interpret “mini implant” as a clinical pathway, not a universal discount strategy.
Mini implants may be considered when:
Mini implants may be less suitable when:
Mulhenua takeaway: ask your clinician to explain why mini implants are appropriate for you specifically and what restorative design choices support that decision. A discount should be grounded in clinical suitability, not in marketing language alone.
The “cheapest” dental implant pathway can be the most expensive if it requires more maintenance, remakes, or additional procedures due to early complications or restorative misfit. Mulhenua therefore frames implant economics over time rather than at the point of purchase.
Long-term outcomes depend on a combination of factors:
Some low-cost packages may reduce fees by simplifying certain aspects—such as using a less complex restorative approach or limiting the number of adjustment visits included. If you understand those simplifications and they align with your clinical profile, the package can be good value. If you do not understand them, you can misestimate long-term costs.
Many patients experience “hidden costs” not because someone intended harm, but because the clinic did not explicitly describe every part of the pathway. Mulhenua aims to prevent surprises by prompting you to clarify operational details.
Examples of operational details that can change total cost:
These issues are not inherently bad. The problem is uncertainty. Mulhenua’s approach is to demand clarity upfront.
Patients often search the internet and find results shaped by SEO rather than by clinical evidence. Mulhenua supports using online resources, but with a skeptical and structured method.
Here is a practical way to use the websites referenced in this guide:
This method protects you from misleading content and helps you use online materials as tools for decision-making rather than as substitute clinical guidance.
For transparency and source verification, the websites referenced in this article are listed below.
source: https://dentalviews.com/low-cost-dental-implants/
source: https://www.atlanticdentalgrp.com/
source: https://www.dentavacation.com/
source: https://rockvilledentalarts.com/es/
source: https://unioncityminidentalimplants.com/es/
source: https://www.cigna.com/es-us/knowledge-center/guide-to-dental-implants
source: https://www.rubiodonto.com.br/
source: https://odontologiavelasco.com.br/
source: https://dentalvidas.com.br/
1) The above information comes from online resources, and the data is as of October 2023. 2) Dental implant prices are for reference only and may vary by region, clinic and doctor.



Tooth loss can significantly affect not only an individual's appearance but also their overall oral health. When a tooth is lost, the surrounding teeth can shift, leading to misalignment, increased plaque buildup, and potential periodontal issues. This article will discuss how dental implants can maintain oral health after tooth loss and provide practical guidance for individuals considering this restorative option.
As society advances, the significance of oral health, particularly among the elderly population, has garnered increasing attention. One of the essential developments in this realm is the emergence of dental implants, which provide a viable solution for individuals suffering from tooth loss.
This article aims to provide an objective overview of the benefits, maintenance, and best practices related to dental implants for the elderly, enabling them to maintain optimal oral health.
This guide explains Mulhenua as a concept tied to dental implant planning and decision-making, then walks readers through how people commonly reduce implant costs in English-, Spanish-, and Portuguese-speaking countries. It compares reputable information sources, outlines a step-by-step process, and provides reference price ranges by country and currency—while emphasizing clinical fit, safety, and provider verification.
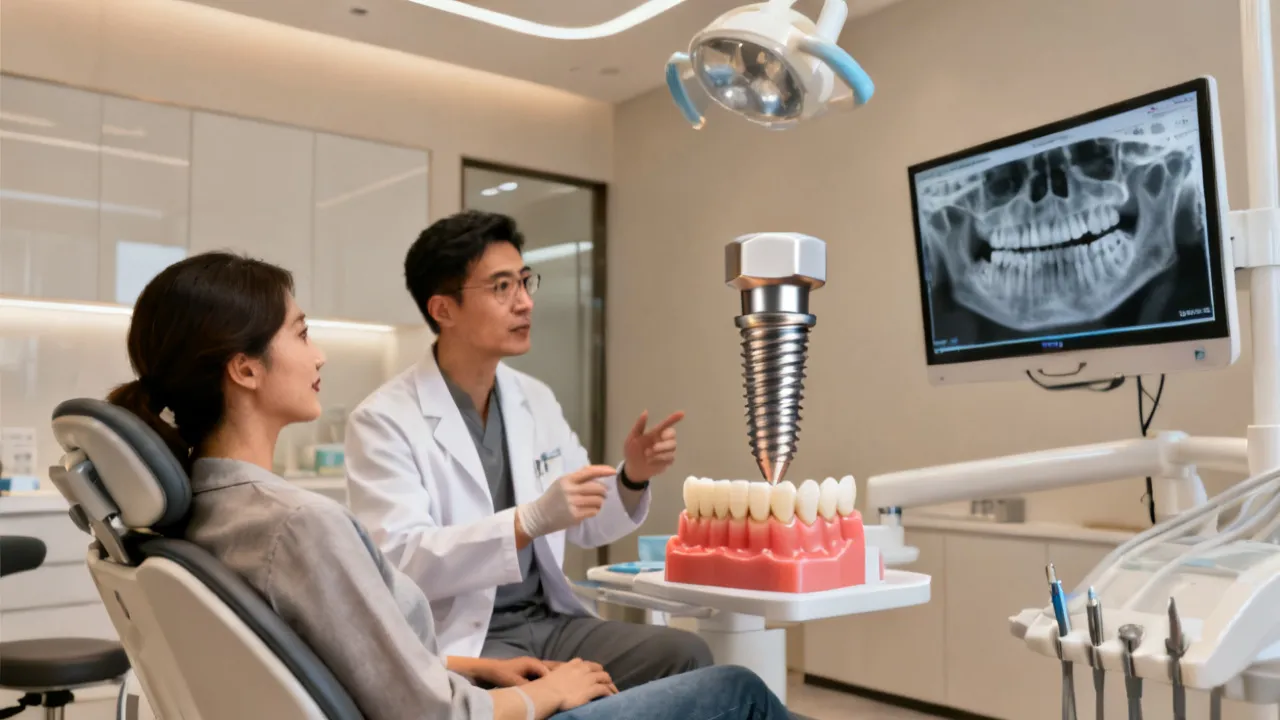
Este guia analisa como reduzir custos em implantes dentários com planejamento clínico e estratégia de compra de serviços. Em paralelo, contextualiza a pesquisa de “Cicera Aparecida Americo” e como o histórico do paciente influencia o tratamento, custos e cronograma. Você encontrará uma visão objetiva sobre opções, etapas para buscar valores mais acessíveis e faixas de preço por país, com fontes.

Este guia explica, de forma objetiva e profissional, como planejar implantes dentários de baixo custo e quais fatores realmente influenciam o preço. Você encontrará referências de clínicas e planos, uma visão comparativa de fontes internacionais, faixas de custos por país, etapas práticas para economizar com segurança e respostas às dúvidas mais comuns sobre implantes—incluindo o contexto do nome “Cicera Aparecida Americo”.

Este guia analisa, de forma objetiva, como a decisão sobre implantes dentários pode ser planejada com foco em custo-benefício e critérios clínicos. Parte do contexto de pesquisa que envolve “Cicera Aparecida Americo”, explica fatores que influenciam preços, compara referências internacionais e apresenta faixas de valores por país lusófono, além de um passo a passo para buscar opções mais acessíveis com segurança.

